What exactly is the Anion Gap?
The anion gap is a calculated value used in blood chemistry to gauge electrolyte levels and pH status. It comes from a standard serum chemistry panel and reflects the relationship between measured positively charged ions and negatively charged ions in the blood. In practical terms, MUDPILES mnemonic memory aid it is a valuable diagnostic marker that can support clinicians look for hidden problems involving unmeasured charges.
Typically, the anion gap is derived from the electrolyte test, BMP, or CMP. These tests assess key values such as serum sodium, serum chloride, and serum bicarbonate. Since the body carefully regulates anion levels, changes in these numbers can provide clues about a possible metabolic problem or other acid-base issues.
The anion gap is not a diagnosis by itself. Instead, it is a screening test that helps guide clinical interpretation. A result that is elevated or decreased may suggest an acid-base disorder, but the meaning depends on the full clinical picture, other labs, and the patient’s symptoms.
How the Anion Gap Calculator Functions
An anion gap calculator determines the gap using commonly available laboratory values. Typical inputs are sodium, chloride, and bicarbonate. These represent the core values used to approximate the difference between measured cations and measured anions in the blood.
The calculator is designed to make the process fast and uniform. By entering the sodium level, chloride level, and bicarbonate level from a laboratory result, the calculator gives a number that can be compared with the lab reference range or reference interval. Some tools also allow optional input of potassium, though it is not always included in the standard formula.
This can be especially useful when reviewing a serum chemistry report and trying to determine whether there is evidence of metabolic acidosis or another acid-base disorder. The calculator reduces the arithmetic, but it does not replace professional judgment. A calculated value still needs context, including the rest of the blood chemistry and the patient’s condition.
The key strength of an anion gap calculator is efficiency and consistency. It helps limit manual errors and provides a quick estimate of whether the result appears within the expected range, borderline, or abnormal. Still, a calculator is only as good as the data entered, and any measurement error in the lab values can affect the final result.
Anion Gap Formula and Calculation Steps
The usual anion gap formula is often written as Na minus (Cl + HCO3). In this formula, Na indicates serum sodium, Cl indicates serum chloride, and HCO3 stands for serum bicarbonate. This calculation provides an approximation of the difference between major measured ions in the blood.
In some settings, potassium may be included in the formula. A potassium-inclusive version may be written as:
(Na + K) - (Cl + HCO3)
However, many clinical settings use the simpler version without potassium because the result is more convenient to interpret and potassium contributes only a little to the overall calculation. Whether potassium is included depends on the lab method and the clinical preference for that particular calculation formula.
Here is a basic calculation example using the standard formula:
- Sodium: 140 Chloride: 104 Bicarbonate: 24
Step 1: Sum chloride and bicarbonate: 104 + 24 = 128
Step 2: Deduct that total from sodium: 140 - 128 = 12
The anion gap in this example is 12. That number is then evaluated with the lab’s lab reference range to determine whether it appears normal, high, or low. This type of arithmetic is exactly what an anion gap calculator automates.
Understanding the formula helps with something beyond computation. It also helps explain why shifts in chloride or bicarbonate can strongly influence the final result. A lower bicarbonate level, for example, can increase the anion gap and suggest acid retention or loss of buffer in the body.
What a Elevated Anion Gap Can Indicate
A high anion gap often suggests metabolic acidosis, which is a condition where acid accumulates or bicarbonate is used up. In this context, the body has more unmeasured acids in the bloodstream than expected, and the gap widens because those ions are not directly counted in the basic calculation.
One classic cause is lactate buildup, where lactate builds up due to poor oxygen delivery, shock, severe illness, or intense metabolic stress. Another common cause is ketoacidosis, which can occur in diabetes, prolonged fasting, or alcohol-related illness. In both cases, the elevated gap reflects excess acid production.
Impaired kidney function can also lead to a high anion gap because the kidneys are less able to excrete acid and other waste products. As these substances collect, the blood chemistry may show a rising gap along with other abnormalities such as increased creatinine or reduced bicarbonate.
Other contributors may include toxin exposure, severe dehydration, or advanced metabolic disorder states. The important point is that a high gap is a clue, not a final diagnosis. It indicates that something is altering acid-base status, and further evaluation is often needed.
When reviewing a high result, clinicians often look at the full pattern of serum chemistry values. A lower bicarbonate level, elevated lactate, abnormal glucose, or worsening kidney markers can strengthen the case for a true acid-base disorder. In contrast, a one-time unexpected result may reflect laboratory variation or a sample issue.
How a Reduced Anion Gap May Indicate
A reduced anion gap is less common than a elevated one, but it can still be medically significant. One of the most common explanations is hypoalbuminemia, which means a decreased albumin level. Albumin carries a negative charge, so when albumin drops, the calculated gap can also drop.
Paraproteinemia is another possible explanation. In this case, abnormal proteins in the blood may disrupt the measured charge balance and decrease the gap. This can happen in disorders where a monoclonal protein is present, and it may call for additional testing if the lab pattern fits.
A low gap can also be caused by laboratory error or other forms of measurement error. A sample mix-up, instrument issue, or inaccurate chloride reading can produce a result that looks abnormal even when the underlying physiology is not. For that reason, unexpected low results often merit repeat testing or careful review.
Because albumin affects the calculation so strongly, a low anion gap should not be interpreted without checking the albumin level. The result may be “low” only because the patient’s protein status has changed. In some cases, an albumin-related correction brings the value back into a more suitable range.
Typical Anion Gap Spectrum and Diagnostic Context
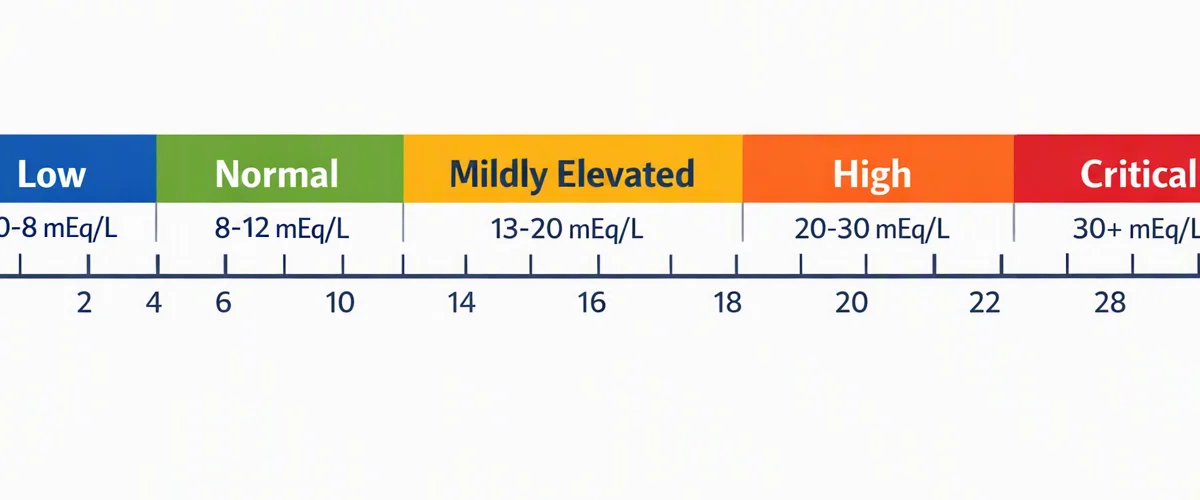
The normal range for the anion gap depends on the testing procedure and the device used. That means the lab reference range may differ between facilities, and a number that is considered normal in one place may be borderline high in another. That is why the exact reference interval from the testing lab matters.
Another important concept is the albumin-corrected anion gap. As albumin influences the result, a low albumin level can make the gap seem falsely low. Adjusting for albumin gives a more accurate corrected value in patients whose protein status is abnormal. This is especially useful when trying to decide whether there is hidden metabolic acidosis.
Lab variation also affects interpretation. Different analyzers, reagents, and reporting methods can shift the expected range slightly. As a result, the same blood chemistry result may need to be interpreted differently depending on the laboratory and the clinical setting.
Medical interpretation should always consider symptoms, the rest of the serum chemistry, and the likely diagnosis. A number by itself is not enough. A result near the upper end of normal may be unremarkable in one patient but concerning in another if there are signs of illness, elevated lactate, or other acid-base changes.
In practice, the anion gap works best as one piece of the larger diagnostic picture. It is a useful screening test, but it becomes more meaningful when paired with the patient’s history, medications, and other laboratory findings.
How to Interpret Outputs Together with Other Laboratory Tests
The most helpful anion gap interpretation comes from using it with other tests. An arterial blood gas can reveal whether the body is too acidic or alkalemic and whether respiratory compensation is occurring. This helps clarify whether the blood chemistry abnormality truly indicates an acid-base disorder.
Serum lactate is especially important when a high anion gap raises concern for lactic acidosis. If lactate is elevated, that finding supports excess acid production and can help pinpoint the underlying cause. Similarly, glucose is essential when evaluating possible ketoacidosis, especially in diabetic patients.
Creatinine provides key information about renal function. If creatinine is elevated, kidney failure may be contributing to the abnormal gap. This is one reason the anion gap is often reviewed alongside a more complete metabolic panel rather than in isolation.
When these results are interpreted together, the pattern becomes more meaningful. For example, a high gap with low bicarbonate, high lactate, and abnormal arterial blood gas values points firmly toward metabolic acidosis. A low gap with low albumin may be less alarming if the albumin-corrected anion gap is normal.
In other words, the calculator gives a number, but the other labs explain the story. That is why professional clinical interpretation remains important, especially when the laboratory result is borderline or the patient is clearly unwell.
When to Seek Medical Evaluation
Any abnormal anion gap should be assessed in light of the situation, especially if there are alarming symptoms. Shortness of breath, disorientation, vomiting, labored breathing, severe fatigue, dehydration, chest pain, or altered mental status can all suggest a more serious acid-base problem.
If the result is unexpectedly high or low and the person is unwell, urgent care or prompt medical attention may be necessary. A possible acidosis can become dangerous if it signals an untreated underlying illness such as infection, diabetic crisis, kidney dysfunction, or toxin exposure.
This is why anion gap calculator should be viewed as a tool for support, not self-diagnosis. The calculator can help organize a blood chemistry result, but it cannot determine the cause on its own. A medical professional can assess the full picture, repeat testing if needed, and decide whether additional workup is appropriate.
If you are looking at a laboratory report and the result seems abnormal, the safest next step is to talk about it with a clinician who can interpret the number alongside the rest of the electrolyte panel, the patient’s history, and the exam findings.
Frequently Asked Questions About Anion Gap Calculation
How can you calculate the anion gap from blood chemistry?
Apply the usual anion gap formula: sodium minus the sum of chloride and bicarbonate, written as Na minus (Cl + HCO3). Most anion gap calculator tools do this automatically when you enter the serum sodium, serum chloride, and serum bicarbonate from the blood test.
What is regarded as a normal anion gap?
A normal result depends on the lab reference range used by the specific laboratory. Because of lab variation and different measurement methods, the normal reference interval is not identical everywhere. Always compare the result to the range printed on the report and take into account the full clinical context.
What causes a elevated anion gap?
A high anion gap is commonly associated with metabolic acidosis. Usual causes include lactic acidosis, ketoacidosis, and kidney failure. Other causes may include certain toxins or severe illness. The result should be reviewed alongside other labs and symptoms.
Can a low anion gap be serious?
Yes, a decreased anion gap can sometimes point to an important issue such as hypoalbuminemia, paraproteinemia, or lab error. It is usually less urgent than a high gap, but it should not be dismissed if it is persistent, unexplained, or accompanied by symptoms or other abnormal blood chemistry findings.
Why is albumin correction important for anion gap results?
Albumin affects the charge balance in blood, so low albumin can make the anion gap appear lower than it really is. Using the albumin-corrected anion gap helps provide a more accurate corrected value and improves clinical interpretation, especially when evaluating possible hidden metabolic acidosis.