How an Anion Gap Calculator Calculates
An anion gap is a quick way to check acid-base balance using routine electrolytes. An anion gap calculator helps you calculate anion gap from routine lab values, usually sodium, chloride, and bicarbonate. In various settings, this acts as a practical diagnostic tool for detecting a hidden metabolic disturbance and informing the next step in lab interpretation.
The concept is basic: measured positive ions and measured negative ions do not fully account for all charged particles in the blood. The “gap” represents unmeasured ions, and changes in that gap can provide important clinical significance. A high value often points to an acid buildup state, while a low value may suggest protein-related changes or lab issues. Used well, the calculator is a screening metric that supports broader acid-base evaluation.
Because the result depends on common serum electrolytes, it can be checked easily from a basic metabolic panel. That makes it useful for a quick assessment when a patient has symptoms or labs that suggest acid-base disorders. The result should always be interpreted in context, not in isolation.
How to Calculate the Anion Gap
The standard anion gap formula relies on the recorded ions in the blood. In most cases, it is computed as:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also add potassium in the calculation, though many laboratories and bedside tools exclude it because the difference is usually small. Whether potassium urine anion gap formula is used depends on the method and the lab convention. The main point is to know which version your result reflects before you interpret results.
The values originate from a basic metabolic panel, which provides a rapid snapshot of major electrolytes. The panel typically includes sodium, chloride, bicarbonate, and sometimes potassium. Since these results are widely available, the anion gap calculator works well as a quick clinical interpretation aid when reviewing a patient’s electrolyte panel.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That number alone is not the diagnosis, but it is a useful clue. A structured way to use the calculator is to:
- Review the basic metabolic panel for the major electrolytes. Verify the units and calculation method used by the lab. Check whether potassium is included. Contrast the result with the lab’s reference range. Consider whether the pattern suggests a metabolic acidosis or another acid-base disorder.
In practice, the calculator is most helpful when used as part of a broader clinical picture rather than as a standalone number.
Typical Anion Gap Range and Assessment
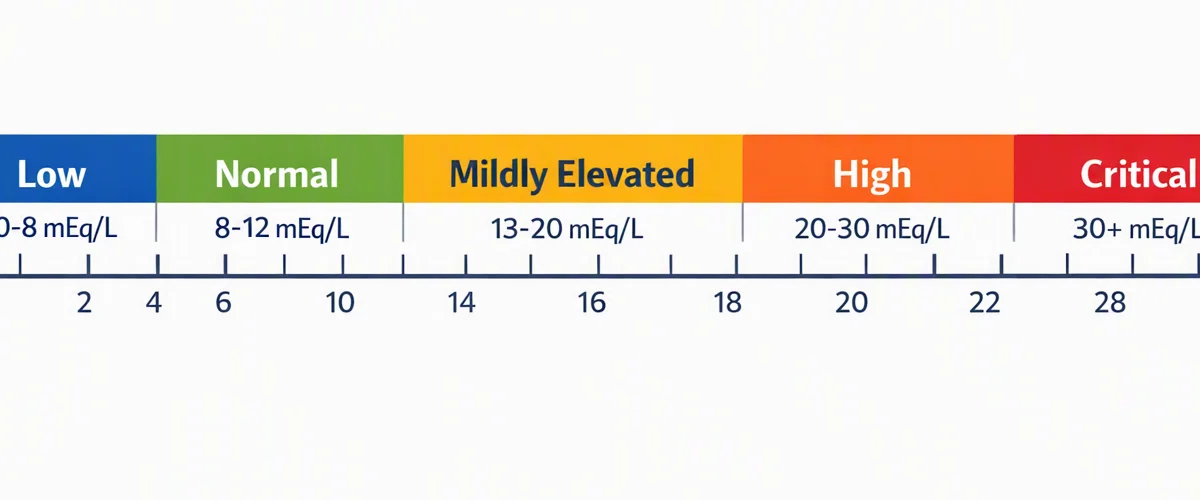
The normal range for the anion gap is influenced by the lab method and the reference range reported by the facility. Different analyzers, different electrolyte measurement techniques, and different inclusion of potassium can all alter the expected value. That is why the number should always be matched to the specific laboratory’s reference interval.
A normal anion gap does not automatically mean everything is fine, and an abnormal gap does not automatically mean one specific diagnosis. Instead, the number points to the type of metabolic acidosis or other acid-base disorders present. A normal gap with acidosis often points toward bicarbonate loss or chloride retention, while an elevated gap suggests unmeasured acids have accumulated.
Albumin matters because it is a major unmeasured anion. When serum albumin is low, the measured anion gap may appear falsely normal or only mildly elevated even when clinically important acid accumulation is present. That is why the raw number must be judged alongside the patient’s albumin level and overall presentation.
As a practical rule, if the clinical picture suggests acidosis but the anion gap is not clearly elevated, consider whether reduced albumin is masking the result. This is where the corrected value becomes useful. The calculator is most helpful when it supports a careful review of acid-base disturbances rather than replacing that review.
Frequent Causes of an Elevated Anion Gap
An elevated anion gap often indicates high anion gap metabolic acidosis. This shows the body has accumulated acids that are not fully reflected in the routine electrolyte measurements. Recognizing this pattern early can focus the differential and guide the next steps in evaluation.
Some common causes are:
- Lactic acidosis, which can occur when tissues are poorly perfused or when lactate production increases. Ketoacidosis, seen with diabetic ketoacidosis, starvation, or alcohol-related ketosis. Renal failure, where impaired acid excretion allows organic acids to build up. Toxic alcohols, which can produce dangerous metabolic derangements and require urgent attention.
Lactic acidosis is a classic cause of a high anion gap and should be considered when there is shock, oxygen deprivation, infection, or severe physiologic stress. Ketoacidosis is another frequent cause, especially when glucose, ketones, and volume status support that diagnosis. Renal failure can contribute by reducing the body’s ability to clear acids, and toxic alcohols may create a particularly serious and time-sensitive presentation.
A high result should prompt a focused review of presenting complaints, medications, toxic exposures, hemodynamic status, glucose, lactate, kidney function, and ketones. The anion gap calculator helps reveal the pattern, but the cause still requires clinical correlation.
Frequent Causes of a Normal-Gap Metabolic Acidosis
A normal gap does not exclude acidosis. In normal anion gap metabolic acidosis, bicarbonate is reduced but chloride increases to preserve electrical balance. This pattern is also called hyperchloremic acidosis because of the associated hyperchloremia.
Frequent causes include diarrhea, renal tubular acidosis, and other conditions that lead to bicarbonate loss. These disorders typically do not raise unmeasured acids the way high-gap states do, so the anion gap may stay within the usual reference range.
Diarrhea can cause significant gastrointestinal loss of bicarbonate. Renal tubular acidosis reflects reduced renal handling of acid or bicarbonate and often presents with a normal anion gap and abnormal urine studies. In both cases, the pattern may be missed if the anion gap calculator is used without a broader acid-base review.
When the result suggests normal-gap acidosis, think about:
- Continued gastrointestinal bicarbonate loss Renal acidification problems such as renal tubular acidosis Hyperchloremia from fluid administration or salt retention Medicine effects and mixed disorders
Here, careful lab interpretation matters. The anion gap is a clue, not the full answer.
Albumin Adjustment and Why It Matters
Serum albumin is one of the most important variables affecting the anion gap. Because albumin carries negative electrical charge, low levels can lower the measured gap even when clinically significant acids are present. That is why hypoalbuminemia can mask a real problem.
Albumin correction modifies the measured value to calculate what the gap would be if albumin were normal. The result is the corrected anion gap. This is especially important in patients with severe illness, malnutrition, liver disease, inflammation, or fluid shifts, where hypoalbuminemia is frequent.
Using the corrected value enhances recognition of acid-base disorders and minimizes false reassurance. A normal-appearing gap in a patient with low albumin may still represent an underlying high anion gap metabolic acidosis. In other words, the correction can expose hidden acid accumulation that the raw number misses.
To use albumin correction well, remember these three points:
- Low albumin decreases the uncorrected anion gap. The corrected anion gap better reflects true acid burden. Correction improves the accuracy of clinical interpretation in complex cases.
For a rapid assessment, the calculator is still helpful without correction, but correct for albumin whenever the result and the clinical picture do not match.
How to Apply the Calculator in a Clinical Setting
The best way to use an anion gap calculator is as part of a current review of the patient’s symptoms, exam, and test results. Begin with the electrolyte panel or basic metabolic panel, then combine the result with a blood gas when available. That process helps determine whether there is true acidemia and whether compensation is appropriate.
If a blood gas or arterial blood gas is available, it can confirm the acid-base status and show whether the patient has respiratory compensation or a mixed problem. The gap then becomes one piece of a larger puzzle. It is especially useful helpful in evaluating a suspected metabolic disturbance when symptoms are vague, such as weakness, confusion, nausea, or rapid breathing.
In clinical practice, the most useful workflow is:
- Review the electrolyte panel and calculate the gap. Evaluate the blood gas or arterial blood gas for pH and ventilation status. Assess whether the result fits metabolic acidosis or another disorder. Search for likely possible causes such as lactate, ketones, kidney dysfunction, or toxin exposure. Leverage the result to direct the diagnostic workup.
This is where the calculator has real value as a diagnostic tool. It can quickly highlight abnormalities, support clinical interpretation, and help prioritize urgent evaluation.
Drawbacks, Pitfalls, and When to Seek More Evaluation
While a frequently used anion gap calculator has significant constraints. A typical or abnormal result can be misleading if the actual electrolyte values are wrong, if the sample is compromised, or if the patient has a complex mixed picture. One of the first issues is lab error, which can skew sodium, chloride, or bicarbonate and produce a false result.
Another major issue is the mixed acid-base disorder. A patient may have multiple process at the same time, such as metabolic acidosis plus respiratory alkalosis, or high-gap acidosis plus a normal-gap process. In these cases, the anion gap alone may not expose the full picture.
That is why an arterial blood gas can be very useful. It explains the pH and ventilation component, while the chemistry panel provides the electrolyte pattern. When the clinical picture is unclear, using both tests together improves accuracy and lowers missed diagnoses.
The anion gap delta can also help detect mixed disorders. If the change in the gap does not match the change in bicarbonate as expected, there may be another metabolic process in addition to the one causing the elevated gap. This is especially important in patients with severe illness or overlapping causes.
Get further evaluation when:
- The value does not fit the symptoms or exam. There is concern for lab error. The patient may have a mixed acid-base disorder. The gap is high and the cause is not obvious. The patient needs urgent assessment for metabolic acidosis or toxin exposure.
Used thoughtfully, the calculator is a helpful screening metric, but it should never replace a full clinical evaluation.
FAQs About the Anion Gap Calculator
How is defined the anion gap and why does it matter?
The anion gap is a computed number that reflects the difference between measured positively and negatively charged ions in the blood. It matters because it helps identify metabolic acidosis and other acid-base disorders. As a simple assessment tool, it can indicate hidden acid accumulation, guide lab interpretation, and assist the search for the underlying cause.
How is calculated the anion gap from lab results?
You usually use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In some cases, potassium is included, depending on the lab method. The values come from a basic metabolic panel or an electrolyte panel, and the result should be reviewed alongside the lab’s reference interval before you interpret results.
What counts as a normal anion gap?
The normal range changes by lab because methods and measurement conventions differ. You should always use the local reference range provided with the report. A number outside that range may suggest a metabolic disturbance, but the result must be interpreted in the context of the patient, the serum electrolytes, and any associated blood gas findings.
Why must the anion gap be corrected for albumin?
The gap should be adjusted because serum albumin is a major unmeasured anion. When albumin is low, the uncorrected value may look normal even when acid is present. Albumin correction gives a corrected anion gap that better reflects the true acid load, especially in patients with hypoalbuminemia and complex acid-base disorders.
What can cause a high or low anion gap?
A high value often suggests high anion gap metabolic acidosis from causes such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A normal-gap acidosis may be due to diarrhea, renal tubular acidosis, hyperchloremia, or bicarbonate loss. A low value can occur with hypoalbuminemia, lab error, or other less common conditions, so it should always be assessed carefully in context.