An Anion Gap Calculator is a practical method to calculate the anion gap from routine lab data. With sodium, chloride, and carbon dioxide results from a typical electrolyte panel, it enables clinicians and students rapidly check acid-base balance and look for patterns that may point to an underlying metabolic acidosis or other acid-base disorder. Because the calculation comes directly from common serum chemistry findings, it is one of the most accessible tools in basic laboratory interpretation.
The value is not a diagnosis by itself. Rather than that, it is a screening and interpretation aid that reflects the relationship between measured serum electrolytes and the unmeasured ions in the blood. In practice, this makes the anion gap a useful diagnostic tool for reviewing a result in the context of the patient’s symptoms, history, and other laboratory values.
What the Anion Gap Measures
The anion gap shows the difference between the major measured positive ions and negative ions in the blood. It is based on the principle of electroneutrality, which means the body keeps positive and negative charges in balance. Since standard chemistry tests do not measure every ion, the gap approximates the amount of unmeasured anions present in the sample.
In routine clinical use, the anion gap is a useful way to assess whether an abnormality in the blood chemistry may indicate an acid-base disorder. A shift in the gap can point to accumulation of acids, loss of bicarbonate, or changes in other charged particles. That is why it is often discussed alongside serum electrolytes and other markers of acid-base balance.
For many patients, the anion gap is most helpful when reviewing a basic metabolic profile or an electrolyte panel. The calculation can provide a rapid sense of whether the laboratory pattern is normal or whether further evaluation is needed. It is especially helpful in evaluating a possible metabolic disorder that changes the equilibrium of acids and bases.
How to Calculate Anion Gap from Sodium, Chloride, and Carbon Dioxide
The standard Anion Gap Calculator workflow uses 3 values: sodium, chloride, and carbon dioxide. In most chemistry panels, the reported carbon dioxide value is used as a stand-in for bicarbonate. Because bicarbonate is the key measured base in this formula, the carbon dioxide result is critical to the final number.
The simple calculation is:
Anion gap = sodium − (chloride + bicarbonate)
When using a standard lab report, the formula is often written as:
Anion gap = sodium − (chloride + CO2)
That means the calculator takes away the sum of chloride and carbon dioxide from sodium. For example, if sodium is 140, chloride is 104, and CO2 is 24, the calculation is 140 − (104 + 24) = 12. This is a direct calculation that can be performed manually or through an online calculator.
The advantage of this method is its quickness. Because causes decreased anion gap sodium, chloride, and CO2 are part of a common electrolyte panel, the anion gap can be obtained without additional testing. This makes it useful as a fast evaluation step during interpretation of routine laboratory values.
Equation, Units, and Normal Range
The anion gap formula is typically expressed in mEq/L. This unit reflects the charge concentration of the measured ions in serum electrolytes. Most calculators and references report the answer in the same units because the result is derived from concentrations of charged particles rather than mass or volume.
The exact normal range can vary depending on the laboratory method used. Different analyzers, instruments, and reporting conventions can shift the expected value slightly. Many labs consider a typical anion gap to fall within a range that centers around the low teens, but the important point is to use the local reference range that matches the testing method.
This is why the same numerical value may be interpreted differently depending on the clinical setting. An anion gap that appears normal on one report might be borderline or mildly abnormal on another if the lab uses a different calibration or calculation approach. A careful review of the report is part of sound medical decision-making.
In most cases, the formula is best used as a practical guide rather than an absolute threshold. The calculator provides a numerical value, but the meaning of that value depends on the patient’s overall context, the rest of the chemistry panel, and whether the reported carbon dioxide reflects true bicarbonate status.
How to Understand a High or Low Anion Gap
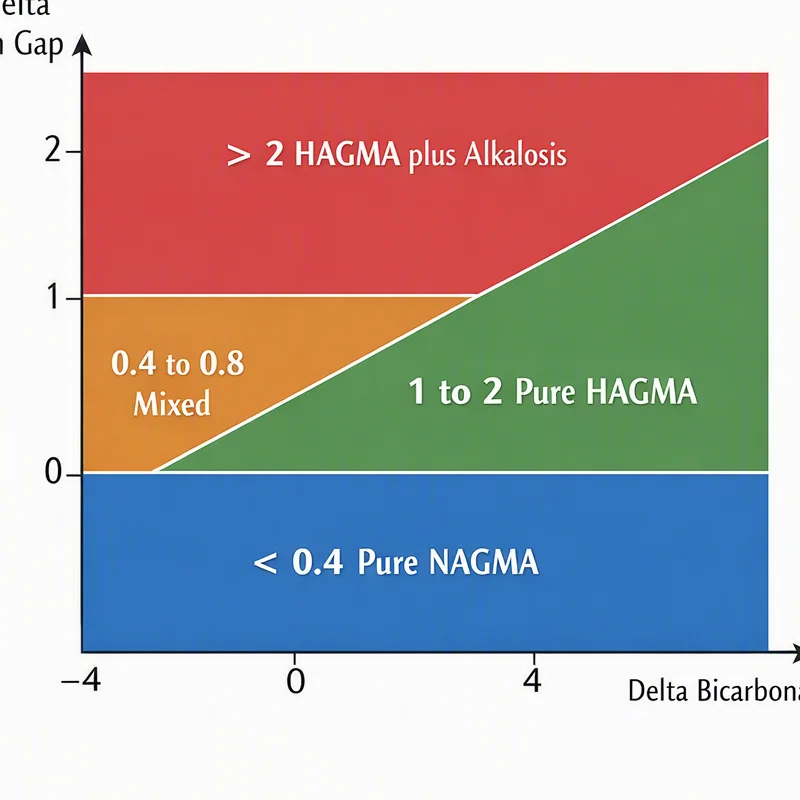
A elevated anion gap often points to the presence of extra acids in the blood. This is a typical clue in metabolic acid buildup, where acid accumulation or reduced acid clearance reduces the balance between measured cations and anions. In practical terms, a high value can suggest a more serious underlying issue that needs further workup.
A expected anion gap does not always rule out an acid-base problem. Some forms of acidosis can occur with a gap that remains within the expected normal range. For that reason, the anion gap should be interpreted together with pH, bicarbonate, chloride, and other findings rather than used alone.
A low anion gap is less common, but it can be clinically meaningful. One major reason is a low level of serum albumin, because albumin contributes negatively charged proteins that affect the balance of measured ions. When albumin is reduced, the observed gap may appear lower even if other processes are present.
Evaluating a gap also depends on whether the patient has a mixed disorder. For example, a person may have metabolic acidosis with a gap that seems only mildly elevated if another process is lowering the bicarbonate or if the electrolyte pattern is altered by treatment or fluid shifts. This is where careful interpretation matters more than the number alone.
Typical Causes of Unexpected Findings
Various conditions can cause a raised anion gap. A well-known cause is lactic acidosis, where lactate increases due to limited oxygen supply, shock, severe illness, or other metabolic stress. Another frequent cause is ketoacidosis, which occurs when ketone bodies accumulate in diabetes, starvation, or other states of impaired carbohydrate use.
Renal failure can also raise the gap because the kidneys are less able to clear acid load and other unmeasured anions. As kidney function worsens, acids accumulate and the measured electrolyte pattern may shift. In this situation, the anion gap becomes one part of a broader evaluation of metabolic waste retention and acid handling.
Toxin ingestion is another important category. Certain ingestions can create a high gap by adding acids or toxic metabolites into the blood. In the right clinical scenario, the anion gap may provide an early clue that prompts urgent investigation. The calculation itself does not identify the toxin, but it can support timely recognition of an abnormal pattern.
On the other hand, a reduced anion gap may be associated with low albumin, laboratory artifact, or uncommon changes in serum proteins and ions. While less frequent than high values, a low result should not be ignored if it is unexpected or inconsistent with the patient’s condition. It may require repeat testing or broader evaluation of the chemistry panel.
Adjusting the Anion Gap for Albumin
Correction for albumin is an key measure when evaluating the anion gap, especially in patients with hypoalbuminemia. Because albumin is a major unmeasured anion, a low albumin level can make the anion gap look falsely normal or low. In these cases, the unadjusted result may underestimate the true acid burden.
An albumin-adjusted anion gap accounts for this effect by modifying the calculated value based on the albumin concentration. The exact adjustment method can differ, but the purpose is the same: to improve accuracy in interpretation when albumin is below normal. This is particularly useful when reviewing suspected metabolic acidosis in hospitalized or chronically ill patients.
The need for correction becomes easier to see when the laboratory pattern seems inconsistent with the clinical picture. For example, a patient may have signs of acid-base disturbance, but the uncorrected gap is not elevated. In that setting, checking albumin and applying correction can help reveal an abnormality that would otherwise be overlooked.
Albumin correction does not take the place of the original calculation. Instead, it adds another layer of information to the same method-based assessment. The adjusted number should still be interpreted with the clinical picture, especially if there are mixed disorders, fluid changes, or multiple abnormal laboratory values.
Limits of an Anion Gap Calculator
While an Anion Gap Calculator is helpful, it has several limitations. One major is lab variation. Multiple analyzers and methods can produce slightly different sodium, chloride, or carbon dioxide values, which changes the final result. That means the same patient could have a slightly different number depending on where the sample is processed.
Measurement error can also influence the outcome. Tiny inaccuracies in any one of the input values can alter the final calculation. As the anion gap is derived from a subtraction-based formula, minor differences in chloride or CO2 may have a meaningful effect on the result, especially if the gap is near the edge of the reference range.
Another limitation is that the calculator reflects only a portion of the acid-base picture. It does not directly measure blood pH, lactate, ketones, renal function, or toxic substances. For that reason, the number should be treated as one part of broader blood test interpretation, not as a stand-alone answer.
The best use of the tool is as a fast screening aid. It can identify a possible abnormality and guide further evaluation, but it cannot determine the cause on its own. The same numerical value can have distinct meaning depending on the patient’s symptoms, medications, hydration status, and underlying illness. Effective medical decision-making always combines the calculation with the rest of the clinical picture.
FAQs
How do you calculate the anion gap using sodium, chloride, and CO2?
Calculate with the formula sodium − (chloride + CO2). In this calculator workflow, carbon dioxide is used as a useful substitute for bicarbonate. The result is the anion gap, usually reported in mEq/L.
What is the normal range for an anion gap?
The normal anion gap depends on the laboratory and method used. That is why you should always compare the result to the report’s reference range. Different serum chemistry analyzers can generate slightly different expected values.
What is a high anion gap mean?
A elevated anion gap commonly suggests metabolic acidosis resulting from extra unmeasured acids in the blood. Typical causes include lactic acidosis, ketoacidosis, renal failure, and some cases of toxin ingestion.
What causes the anion gap be low?
A low anion gap is frequently associated with low albumin, especially in hypoalbuminemia. It can also result from lab-related issues or less common changes in serum proteins and electrolytes. When the result is unexpected, repeat testing and broader evaluation may be appropriate.
Should albumin be taken into account when reading the anion gap?
Yes, it should. Albumin correction is important because albumin is a major unmeasured anion. When albumin is low, the measured gap may underestimate the true abnormality. An adjusted anion gap can improve interpretation and make the result more useful for assessing acid-base balance.