Understanding the Anion Gap?
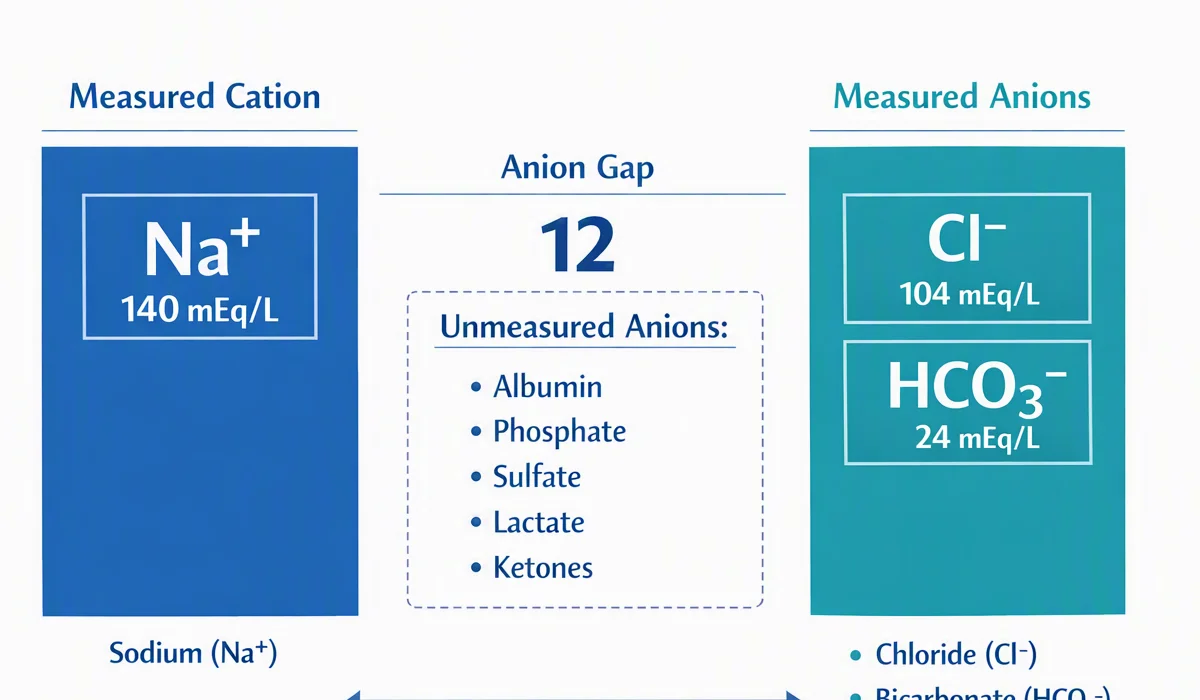
The anion gap is a measure used in acid-base interpretation to approximate the amount of unmeasured anions in the blood. It is usually derived from routine serum electrolytes, especially sodium, chloride, and bicarbonate. In simple terms, the anion gap calculator helps clinicians see whether there are extra acids in the bloodstream that are not directly measured on a standard metabolic panel.
Most of the time, the formula is based on sodium minus chloride and bicarbonate. Because sodium is the main measured cation and chloride and bicarbonate are the main measured anions, the gap reflects the difference between what is measured and what is not. A unexpectedly high result suggests an elevated anion gap, which often points to acid accumulation from conditions that produce organic acids or other unmeasured acid load.
This matters because the anion gap is not a diagnosis by itself. It is a pattern. A high value warrants a search for causes of high anion gap metabolic acidosis, but the result must always be interpreted with the rest of the clinical picture, including serum bicarbonate, pH, and the patient’s symptoms.
Albumin is especially important because it is a major unmeasured anion. If albumin is low, the anion gap may appear falsely normal. That is why an albumin-corrected anion gap is often more accurate than the raw number. This type of gap correction helps refine laboratory interpretation and avoids missing clinically important acidosis.
How Methanol Causes High Anion Gap Metabolic Acidosis
The direct answer is yes: methanol can cause an elevated anion gap During methanol poisoning, methanol itself is not the main acid problem initially. Rather, methanol is metabolized into formic acid, which is toxic and drives metabolic acidosis. When formic acid accumulates, the body’s acid-base balance moves toward systemic acidosis, and the anion gap rises because those acids are not directly measured by routine labs.
This is why methanol is one of the classic toxic alcohols associated with an elevated anion gap. The process begins after toxic ingestion or other exposure, when alcohol dehydrogenase converts methanol into formaldehyde and then to formic acid. Formic acid is the key driver of the metabolic derangement. As it builds up, it uses up bicarbonate, lowering bicarbonate and producing a high anion gap state.
The chemistry also explains why symptoms may be delayed. Early after ingestion, the anion gap may not be very high yet, especially if methanol has not been fully metabolized. Later, as more formic acid accumulates, the gap often rises and acidosis becomes more obvious. This time course is important for clinical suspicion and for deciding when to pursue a full diagnostic workup.
Methanol toxicity also causes characteristic end-organ effects. Because formic acid is especially harmful to the optic nerve and retina, patients may develop visual disturbances, blurred vision, or other signs of ocular toxicity. These findings, combined with acid-base abnormalities, create a strong concern for a toxic ingestion that requires emergency attention.
How to Interpret an Anion Gap Calculator Output
An anion gap calculator is useful, but the result should not ever be read by itself. A “normal” value does not necessarily mean there is no toxic alcohol exposure, and a high value does not prove methanol. The first step is to match the result with the expected range used by the lab and then evaluate whether the patient has metabolic acidosis as shown by low bicarbonate, low pH, or both.
A normal anion gap suggests there is no obvious accumulation of unmeasured acids at that moment, but it does not rule out early methanol exposure. If the patient presents shortly after ingestion, serum methanol may still be present before significant formic acid production. In that setting, the osmolar gap may be more helpful initially, while the anion gap rises later as metabolism progresses.
Albumin must be considered in any serious interpretation. Low albumin lowers the baseline gap, so a patient with substantial acid load can appear deceptively normal. Using an albumin-corrected anion gap can reveal an abnormality that the uncorrected calculation misses. This is a key point in accurate acid-base interpretation and should be part of every careful review of serum electrolytes.
There are also practical nuances:
- A rising gap over time is often more concerning than a single snapshot. Low bicarbonate with a modest gap may still reflect significant acid-base disease. Mixed disorders can blur the picture, especially in critically ill patients. Clinical context counts more than the calculator alone.
In short, the anion gap calculator is a screening and interpretation tool. It helps detect whether there are unmeasured anions consistent with toxic ingestion, lactic acid production, or another cause of metabolic derangement, but it should be paired with blood gas analysis, osmolality, and bedside assessment.
Typical Laboratory Findings in Methanol Toxicity
Several laboratory findings commonly show up together in methanol toxicity. One of the most important is an higher osmolar gap early in the course. This finding reflects the presence of unmeasured osmotically active substances, including methanol itself. As metabolism goes on, the osmolar gap may fall while the anion gap rises, because the parent alcohol is converted into acidic metabolites.
An arterial blood gas is crucial for assessing severity. It helps reveal the degree of acidemia, the respiratory compensation, and whether there is a mixed disorder. In methanol poisoning, blood gas analysis often reveals metabolic acidosis with a low pH and reduced bicarbonate. The pattern may be severe, especially if diagnosis is delayed.
Lactate can be elevated as well, but it should not distract from the main diagnosis. Sometimes a true secondary lactic acidosis develops from tissue hypoxia, shock, or poor perfusion. In other cases, lab artifacts or overlapping illness blur the picture. Either way, lactate does not confirm or exclude methanol by itself.
Bicarbonate is often low because it is used up buffering the acid load. The drop in bicarbonate is one of the reasons the anion gap rises. In severe cases, serum bicarbonate can be extremely depressed, reflecting major systemic acidosis and the need for urgent treatment.
Other useful findings include:
- High serum osmolality or an increased osmolar gap Reduced pH on blood gas analysis Electrolyte abnormalities that affect acid-base interpretation Signs of end-organ injury, including neurologic symptoms or ocular toxicity
When the laboratory pattern is consistent, Click here for more methanol should remain high on the differential, especially if there is concern for toxic ingestion and the patient shows worsening metabolic derangement.
Differential Assessment of High Anion Gap Metabolic Acidosis
Even though methanol is a classic cause, it is only one part of the wider differential diagnosis of high anion gap metabolic acidosis. Many other conditions can create the same pattern, and thorough comparison helps avoid diagnostic error. The most common alternatives include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis is often seen in sepsis, shock, hypoxia, seizures, or severe tissue hypoperfusion. It can produce a high anion gap because lactate is an unmeasured anion. In many patients, it is the main explanation for metabolic acidosis in the hospital setting.
Ketoacidosis occurs in diabetic ketoacidosis, alcoholic ketoacidosis, and starvation states. Ketone bodies act as unmeasured acids and increase the gap. The clinical context, glucose level, and ketone testing help separate ketoacidosis from toxic alcohol exposure.
Uremia from kidney failure can also produce a high anion gap. When the kidneys cannot clear acid effectively, multiple retained solutes contribute to the gap. Because renal failure can coexist with other illnesses, it may mask or overlap with toxic ingestion.
Ethylene glycol is another critical toxic alcohol in the differential. It often causes high anion gap metabolic acidosis as well, and the distinction matters because treatment and complications differ. Ethylene glycol may also cause kidney injury and crystal formation, while methanol more strongly raises concern for visual injury.
In real-world settings, the differential diagnosis should be organized by the clinical picture, the osmolar gap, blood gas findings, ketones, kidney function, and exposure history. No single value replaces thoughtful acid-base interpretation.
When Methanol Should Be Suspected
Suspicion of methanol should arise when a patient has unexplained acidosis plus a compatible exposure history or symptom pattern. The key clue is a history of ingestion or possible access to contaminated alcohol or industrial products. Because patients may not always provide a clear history, the clinician must often rely on secondary findings.
Symptoms suggesting methanol exposure include visual symptoms such as blurred vision, “snowfield” vision, or decreased acuity. These findings are highly concerning because they point toward formic acid toxicity and possible ocular injury. The presence of neurologic symptoms such as headache, confusion, ataxia, or deteriorating consciousness also raises suspicion.
Central nervous system depression can occur in severe poisoning and should be treated as an emergency. A patient may appear intoxicated, but the severity of the acidosis is often out of proportion to a simple ethanol effect. That mismatch is one reason methanol and other toxic alcohols deserve immediate consideration.
Other clues include:
- Elevated anion gap without explanation with low bicarbonate Increased osmolar gap in the right setting Progressive worsening after an apparent delay Possible exposure from a toxic ingestion
Because the presentation can be nonspecific at first, methanol is often a diagnosis of clinical suspicion supported by laboratory evidence. Early recognition is key to preventing severe acidosis, vision loss, and organ failure.
Treatment Summary
Care of methanol poisoning requires prompt action and should begin immediately after the diagnosis is suspected. The main antidote therapy is fomepizole, which prevents the action of alcohol dehydrogenase and stops methanol from being converted into formic acid. By stopping this metabolic pathway, fomepizole helps limit worsening acidosis and toxic metabolite formation.
Hemodialysis may be needed when acidosis is severe, methanol levels are high, visual symptoms are present, or the patient is clinically unstable. Dialysis removes methanol and formic acid directly and also corrects acid-base abnormalities. It is a critical intervention in severe poisonings and is often used in combination with the antidote.
Sodium bicarbonate is frequently used to help treat severe acidosis and support acid-base balance. It does not remove the toxin, but it can short-term improve pH while definitive therapy is arranged. The decision to give bicarbonate depends on severity, pH, and the full clinical situation.
Supportive care remains essential. This includes airway management if needed, monitoring of electrolytes and blood gas values, treatment of complications, and careful reassessment. Because patients can deteriorate quickly, methanol poisoning is an emergency evaluation scenario rather than a watch-and-wait problem.
In general, treatment aims to stop toxic metabolism, remove the poison, and steady the patient while the diagnostic workup continues.
Frequently Asked Questions: Methanol and Anion Gap
Can methanol cause a raised anion gap?
Yes. Methanol can produce a high anion gap because it is converted into formic acid, which leads to high anion gap metabolic acidosis. The rise in the gap reflects unmeasured acids accumulating in the blood as bicarbonate drops.
How does methanol toxicity elevate the anion gap?
Methanol toxicity elevates the anion gap because the body turns methanol into formic acid, an acid that is not directly measured on routine chemistry panels. As acid builds up, bicarbonate is depleted and the gap increases. This is a typical example of acid accumulation and systemic acidosis in toxic ingestion.
What is the difference between an anion gap and an osmolar gap?
The anion gap reflects unmeasured anions and helps identify metabolic acidosis. The osmolar gap reflects unmeasured osmoles in the blood and is often raised early in toxic alcohol exposure. In methanol poisoning, the osmolar gap may be raised initially, then the anion gap increases later as methanol is converted to formic acid.
Can a normal anion gap rule out methanol poisoning?
Not necessarily. A normal anion gap does not rule anion gap clinical significance out methanol poisoning, especially early after ingestion or when albumin is low. The patient may still have methanol in the blood before enough formic acid has formed. That is why clinicians also rely on osmolar gap, arterial blood gas findings, symptoms, and overall clinical suspicion.
What lab tests are most useful when methanol ingestion is suspected?
The most useful tests include serum electrolytes, bicarbonate, albumin for gap correction, anion gap calculator output, osmolar gap assessment, arterial blood gas, lactate, serum osmolality, and toxicology-related testing when available. These results help support diagnosis, guide acid-base interpretation, and help distinguish methanol from lactic acidosis, ketoacidosis, ethylene glycol exposure, and other causes of metabolic acidosis.