What Is the Anion Gap and How Is It Calculated?
The anion gap is a derived measurement that https://anion-gap-widget629.image-perth.org/anion-gap-calculator-for-delta-gap-interpretation aids clinicians evaluate acid-base status from a routine serum chemistry panel. It is calculated from electrolytes and is usually based on the measured concentrations of sodium, chloride, and bicarbonate. In basic terms, it gauges the difference between the main measured cations and anions in blood.
The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some labs add potassium, but potassium is often omitted because its concentration is comparatively minor compared with sodium. Even though the calculation is easy, the result can provide an important diagnostic clue about an underlying electrolyte imbalance, changes in unmeasured ions, or an unexpected finding related to plasma proteins.
A normal result indicates a usual acid-base balance, while a high or low result can point toward a more extensive differential diagnosis. Because interpretation depends on the lab’s methods and analyzer, the reference interval may shift modestly from one institution to another.
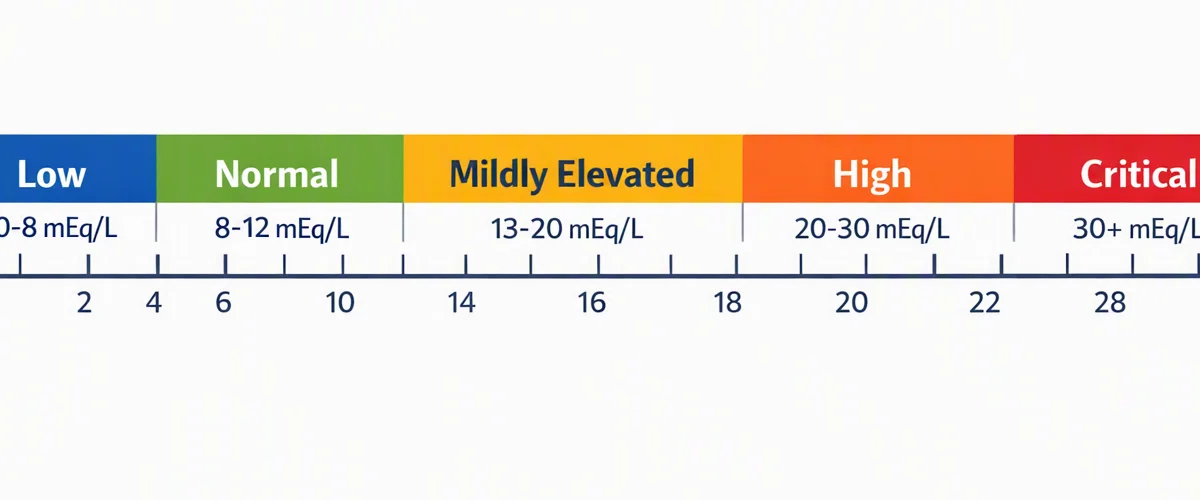
How the Anion Gap Calculator Works
An Anion Gap Calculator performs the calculation using the numbers entered for sodium, chloride, and bicarbonate, and sometimes potassium. This makes it easier to read a lab result rapidly and consistently. The calculator does not identify disease by itself, but it can aid recognize a finding that warrants closer attention.
Because the anion gap is derived from a routine electrolyte panel, the calculation is only as sound as the input values. If the bicarbonate value is inaccurate, or if sodium and chloride are affected by a preanalytic or analytic issue, the computed gap may be misleading. That is why clinicians often rule out artifact before giving too much clinical significance to a single number.
An Anion Gap Calculator is especially useful when the value is beyond the usual reference range. A narrowed anion gap or low anion gap may point to low albumin, excess positively charged proteins, or a testing issue. In practice, the calculator supports detection of a pattern, but the final interpretation rests on the overall clinical picture and whether the value fits in context.
What Is Paraproteinemia?
Paraproteinemia describes the existence of an unusual paraprotein in the blood, typically produced by a single clone of plasma cells. This represents a type of monoclonal gammopathy, which means one clone makes a large amount of one particular immunoglobulin or part of an immunoglobulin, such as a light chain.
These abnormal proteins can be detected because they are different from the polyclonal mixture of normal antibodies. Depending on the condition, the paraprotein may be whole immunoglobulin, free light chains, or an additional abnormal protein product. Some people have no symptoms at first, while others develop manifestations related to organ injury or blood viscosity.
The best known disease associated with paraproteinemia is multiple myeloma, but not every monoclonal gammopathy is malignant. Some cases are discovered incidentally during laboratory testing done for different reasons. Because the paraprotein can change how blood chemistry values read, it may show up as a protein abnormality that alters the anion gap.
Can Paraproteinemia Reduce the Anion Gap?
Absolutely. Paraproteinemia can decrease the anion gap, and a low anion gap may be an useful clue to the presence of a monoclonal gammopathy. The key reason is that some paraproteins are positively charged proteins at normal body pH. When these proteins circulate in sufficiently high amounts, they act as cationic paraproteins and disrupt the balance of measured and unmeasured ions.
In many cases, the decrease is subtle. The anion gap may be only slightly lowered, not necessarily absent. Still, when a low gap appears on an Anion Gap Calculator and the result is not explained by other factors, paraproteinemia becomes part of the differential diagnosis.
This relationship is clinically helpful because the anion gap is not a screening test for paraproteinemia by itself, but it can be a clue that prompts further evaluation. In some patients with multiple myeloma, the low anion gap is one of the first abnormal chemistry findings, especially when combined with anemia, renal dysfunction, or elevated total protein.
That said, a low anion gap is not exclusive. Many other factors can lower it, and a normal gap does not exclude paraproteinemia. The result should be interpreted alongside albumin, total protein, and other laboratory data.
Underlying Mechanisms of a Decreased Anion Gap in Paraproteinemia
Several mechanisms can explain why paraproteinemia decreases the anion gap. The most important is the presence of cationic paraproteins. These paraproteins introduce unmeasured positive charge to plasma, which must be balanced by changes in measured ions such as chloride. As chloride rises to preserve electroneutrality, the calculated anion gap falls.
Hypoalbuminemia often plays a role too. Albumin is a major unmeasured anion, so when albumin is low, the anion gap decreases. In a patient with paraproteinemia, low albumin can intensify the effect and make the gap look even lower. This is why clinicians often correct for albumin when interpreting the result.
Protein binding also matters. Abnormal plasma proteins can change how ions distribute in the bloodstream and can alter the measured relationship between sodium, chloride, and bicarbonate. In some cases, the paraprotein itself may affect assay behavior or distort the chemistry profile through lab interference.
These influences do not all operate the same way in every patient. The specific immunoglobulin class, concentration, and charge properties of the paraprotein all influence the final chemistry pattern. That is why paraproteinemia can be associated with a narrowed anion gap in one case and a seemingly normal value in another.
Other Typical Causes of a Low Anion Gap
Paraproteinemia is an key cause of a reduced gap, but it is not the leading one. Before assuming a plasma cell disorder, clinicians should review other explanations, especially laboratory error. A sample mix-up, contamination, instrument issue, or specimen handling problem can produce an abnormal result that disappears on repeat testing.
Electrolyte abnormalities can also decrease the anion gap. Hypercalcemia can contribute because excess calcium introduces unmeasured cations. Hypermagnesemia can do the same. Another classic cause is lithium, which is a positively charged ion that may reduce the calculated gap when present in sufficient concentration.
Low albumin remains one of the most usual non-artifact reasons for a decreased result. Since albumin is a major unmeasured anion, hypoalbuminemia can produce a decreased gap even without paraproteinemia. That is why the albumin level should always be checked with the chemistry panel.
Because several causes intersect, a low result should not be treated as diagnostic on its own. It is better viewed as a cue to rule out artifact, review the medication list, assess albumin, and consider whether a protein disorder is plausible.
When a Low Anion Gap Should Lead to More Testing
A low gap warrants closer attention when it is ongoing, not explained, or accompanied by other abnormalities. In those cases, the next step often includes repeat testing to make sure that the result is real. Rechecking the chemistry panel can help distinguish a one-time issue from a reproducible finding.
If the low gap persists and albumin does not explain it, the clinician may order serum protein electrophoresis to look for a monoclonal spike or other abnormal protein pattern. This is a key screening test for paraproteinemia. If the electrophoresis is abnormal or suspicion remains high, immunofixation can identify the specific immunoglobulin type.
Free light chains are also useful, especially when the paraprotein is not easily visible on electrophoresis. Light-chain disease can be missed if only total protein or routine electrophoresis is reviewed. Together, these tests help characterize the protein abnormality and determine whether it fits a benign or malignant process.
The decision to investigate further should be guided by the entire clinical picture, not just the Anion Gap Calculator output. A low anion gap plus anemia, kidney dysfunction, bone symptoms, or elevated total protein is more concerning than an isolated borderline abnormality.
Clinical Clues That Suggest Paraproteinemia
A number of findings can make paraproteinemia more likely. Anemia is frequent because marrow function may be affected or because chronic disease is present. Renal dysfunction can occur when monoclonal proteins damage the kidneys or contribute to light-chain deposition. These clues are often more helpful than the low anion gap alone.
Bone pain is a further classic feature, especially when plasma cell disorders weaken bone structure. Patients may describe ongoing pain, tenderness, or fractures with minimal trauma. In the setting of a protein abnormality, this symptom raises concern for multiple myeloma.
Hyperviscosity may occur when large amounts of paraprotein increase blood thickness and impair circulation. Symptoms can include headache, visual changes, dizziness, or bleeding tendency. Although less common, it is an relevant sign of clinically significant paraproteinemia.
Additional clues include elevated total protein, low albumin, recurrent infections, neuropathy, or an unexplained change in kidney function. When several of these features appear together, the low anion gap becomes a more meaningful diagnostic clue rather than an isolated laboratory curiosity.
FAQ About Paraproteinemia and the Anion Gap
Can paraproteinemia lower the anion gap?
Yes. Paraproteinemia can lower the anion gap, especially when the paraprotein is a positively charged protein. The effect may be modest, but a low anion gap can be a helpful clue that prompts further evaluation for a monoclonal gammopathy.
Why does multiple myeloma sometimes cause a low anion gap?
Multiple myeloma can produce large amounts of monoclonal immunoglobulin or light chains. Some of these proteins behave as cationic paraproteins, which lowers the calculated anion gap. Low albumin in myeloma can lower it additionally.
Can a decreased anion gap be caused by testing error instead of disease?
Absolutely. Laboratory error is a common reason for an unexpected low result. This is why repeat testing is often advised before undertaking an extensive workup. If the value normalizes, artifact becomes more probable than disease.
Should albumin be checked when the anion gap is low?
Certainly. Albumin should be checked because hypoalbuminemia is one of the leading reasons for a low anion gap. Since albumin is a major unmeasured anion, a low value can explain the finding or make paraproteinemia appear more pronounced.
What tests confirm paraproteinemia after a low anion gap?
Typical confirmatory tests include serum protein electrophoresis, immunofixation, and free light chains. These studies help identify and define the abnormal protein, determine whether a monoclonal gammopathy is present, and guide further evaluation.